Case 39
Primary clinician: Anna Paling, DVM, DACVIM (Cardiology)
Supervising clinician: Mark D. Kittleson, DVM, PhD, DACVIM (Cardiology)
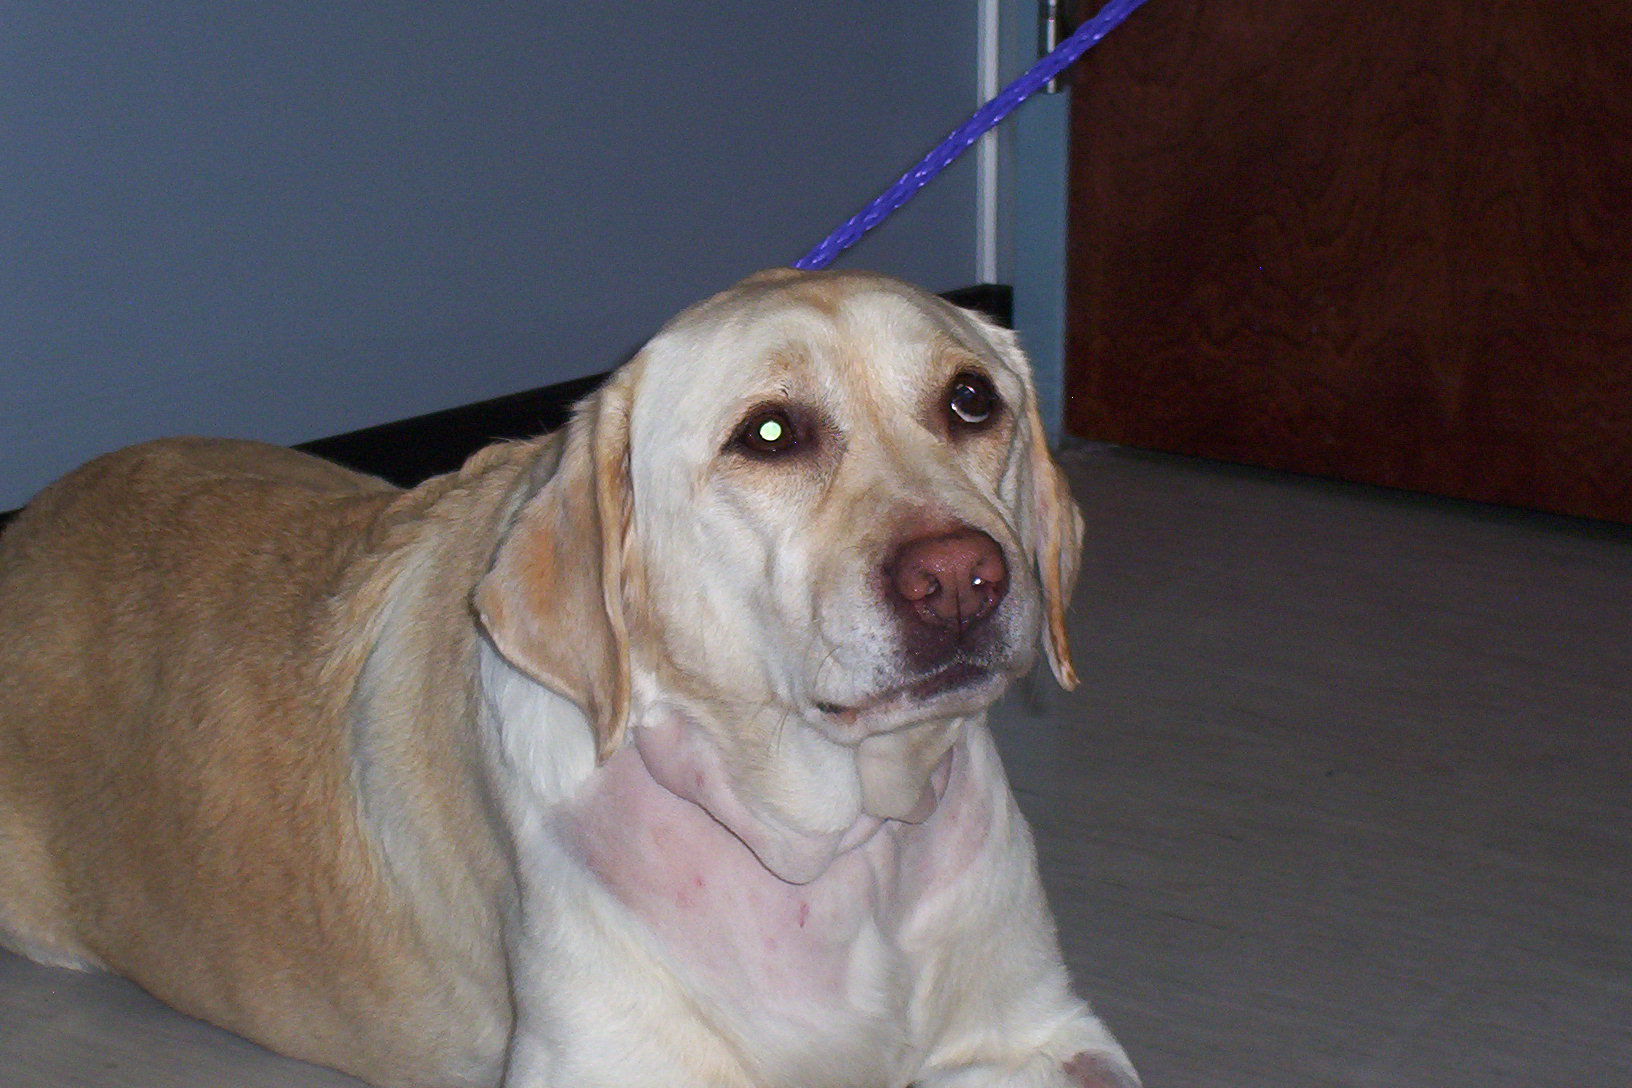
Signalment
- Five-year-old female spayed Labrador Retriever ("Sarah")
Presenting Complaint
- Ascites
Pertinent History
- Sarah was presented to the UC Davis VMTH Cardiology Service for further evaluation and possible treatment of congenital heart disease. Her owner had been in a car accident last summer and his sister took over Sarah's care shortly thereafter. She reports that Sarah would exercise normally and had a normal activity level at that time. After her OVH 3 months ago, Sarah's owner noticed that she began coughing and had some abdominal distension. The abdominal distension has gotten progressively worse since that time. She has also had a progressive reduction in activity level and appetite, and is now exercise intolerant. About twice a month, Sarah has collapsing episodes during which time she seems dazed and confused for about 5 seconds; these are usually brought on by exercise or excitement. The owner has noted collapsing episodes for 6 months but did not know the etiology. The owner has also noticed that Sarah has been having respiratory difficulty for the past month. A heart murmur has not previously been diagnosed.
- PERTINENT HISTORY:
- No pertinent medical history prior to new ownership starting 6 months ago.
- 6 months ago: Presented to first veterinary clinic for walking strangely and possible collapse with activity. No diagnostic workup at that time.
- 4 months ago: Presented because she had two episodes where she fell on her side and staggered. CBC/blood chemistry panel was normal. Ddx - possible epilepsy.
- 3 months ago: OVH
- 3 months ago: Presented to check incision (bruising) and for cough/gag. Owner to monitor.
- 3 months ago: Recheck - still coughing. Rx: Amoxicillin 750mg BID x 14 days. Possible abdominal distention which was not worked up further.
- 1 month ago: Presented to a different veterinary clinic for abdominal distension. Pale mm with prolonged CRT. Low output signs. Ddx: congestive heart failure
- 4 weeks ago: CBC/chemistry panel - normal
- 3 weeks ago: Abdominal ultrasound revealed a large amount of abdominal fluid, moderate hepatomegaly with mottled texture, severe hepatic vein and caudal vena caval distension. Brief cardiac exam revealed severe right atrial enlargement. Recommended evaluation by cardiology specialist.
- 3 weeks ago: Furosemide 80mg BID started by referring DVM. Abdominocentesis attempted but not accomplished.
- 2 weeks ago: Furosemide increased to 80mg TID due to progressive abdominal distention. Benazepril 15mg daily started.
- CURRENT MEDICATION:
- Furosemide 80mg q8 hours
- Benazepril 15 mg q24 hours
- Sarah has not had a successful abdominocentesis performed.
Physical Examination
- GEN: QAR, 5-8% dehydrated based on decreased skin turgor and pale, tacky mm; very weak and lethargic. P=140-150 R=32. Ambulatory x 4 with assistance. Cold extremities.
- INT: Smooth, full hair coat. Salivary staining interdigitally of all paws. 5cmx2cm area of alopecia with raised, thickened dermis over right metatarsals (presumed acral lick granuloma). No evidence of ectoparasites seen.
- EENT: Symmetric face with no muscle atrophy. Clear conjunctiva, anterior chambers, corneas, and scleras OU. PLRs intact, direct and consensual. No ocular discharge noted. Moderate ceruminous debris and erythema AU. Clean dry nose. Pale, tacky mucous membranes. Clean teeth with no dental calculus or plaque. No oral masses or foreign bodies seen.
- MS: BCS 6/9. No lameness noted; strong symmetric gait.
- CV: Muffled heart sounds; difficult to auscult, particularly over right hemithorax. Soft diastolic murmur possibly ausculted over left hemithorax. No systolic murmur ausculted. Extra heart sound ausculted during early diastole. Pulses weak and symmetric. CRT 2.5 seconds. No obvious jugular pulsation, but subcutaneous edema of the neck noted.
- RESP: Mildly tachypneic, no crackles, wheezes, or stridor ausculted. Referred upper airway noises. Short, shallow breathing pattern.
- GI: Abdomen soft and distended, with fluid wave palpable. Non-painful. Hepatomegaly palpated.
- LN: Mandibular, prescapular, and popliteal lymph nodes less than 1 cm.
Problems
- Ascites most likely due to right heart failure
- Clinical signs suggestive of low cardiac output
- Abnormal heart sounds
- Dehydration
Medical/Surgical Procedure
- Abdominocentesis: 4.25 L serosanguinous fluid removed on presentation to Cardiology Service. Fluid was consistent with a modified transudate.