Case 22 — New Murmur
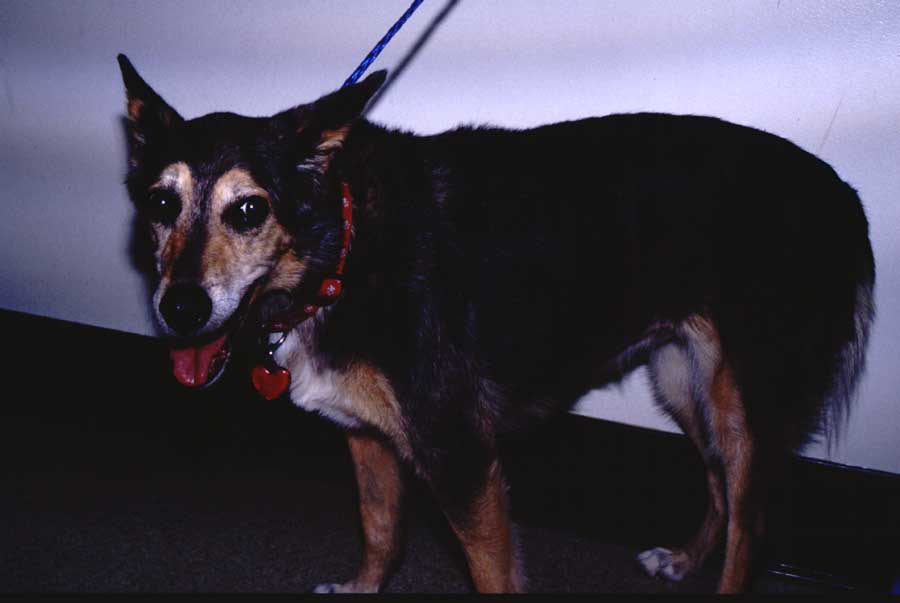
Primary clinician: Janet Aldrich, DVM & Aaron Wey, DVM, DACVIM (Cardiology)
Supervising clinician: Mark D. Kittleson, DVM, PhD, DACVIM (Cardiology)
Signalment
- Species: Canine
- Breed: Australian Shepherd cross
- Age: 13 years
- Sex: Female spayed
- Weight: 20 kg
- Name: Chimere
First Visit
Presenting Complaints
- Non-weight bearing lameness & vomiting
Pertinent History
- Non-weight bearing lame on right front leg since Saturday. Began vomiting Sunday evening; febrile (T = 104.0°F). Owner administered famotidine and Baytril 75 mg. Vomiting has since stopped.
- Shifting leg lameness of long standing. Slowed down over the last year; weak in hind quarters; stumbles when running. Facial twitching and tooth chattering in last 2 weeks.
- Neurology consult revealed underlying neuropathy. On Rimadyl and glucosamine/chondroitin for chronic arthritis.
Physical Examination
- Obtunded and lethargic. T = 104.2°F; P = 120; R = 30.
- CRT = 1.5 sec. Nuclear sclerosis OU. Fractured canines; severe calculus; moderate gingivitis. Serous nasal discharge.
- Non-weight bearing lame on right front. Right lateral metacarpus swollen and painful. Right elbow painful but no effusion. Hip musculature atrophied bilaterally.
- Adequate pulses with occasional dysrhythmia. No murmurs auscultated.
- Exaggerated respiratory pattern; diminished breath sounds right dorsally.
Problems
- Fever/Sepsis
- Vomiting
- Liver disease
- Right forelimb lameness
Visit Summary
Problem 1 (Fever/Sepsis): WBC 21,100 with neutrophilia and left shift. Fibrinogen 600. Urine: 4+ protein, gram-positive cocci. Blood gas: metabolic acidosis with compensatory respiratory alkalosis. Blood and urine culture: pure Staph. intermedius. Started on Timentin 50 mg/kg IV QID.
Problem 3 (Liver disease): ALT 537, Alk Phos 621, cholesterol 597. Possibly due to long-standing carprofen therapy.
Problem 4 (Lameness): Radiographs: soft tissue swelling of lateral metacarpus with irregular bony changes at 4th metacarpal. Elbow radiographs normal. Consistent with possible septic process.
Clinical Diagnoses: Sepsis; right forelimb lameness.
Second Visit (Next Day)
Improving — sternal, drinking on own, no longer obtunded. T = 103.2°F. Culture sensitivities confirm Timentin sensitivity. Antibiotic therapy continued.
Third Visit (Third Day)
Looking brighter. Fever down to 102.6°F. Force-fed without vomiting. Will bear some weight on right forelimb.
New finding: A 3/6 systolic heart murmur auscultated over the mitral valve. Most likely due to vegetative endocarditis as a sequel to sepsis. Echocardiographic evaluation recommended.
Problems: Staph septicemia; right forelimb lameness; 2–3/6 systolic heart murmur.
Discharge: Continue Timentin IV at home (owner is a veterinary technician). Monitor temperature q4h. Rotate every 4 hours.